Anaphylaxis
Board exam relevance: in 1 of 105 exam reports · rank 181- Synonyms
- anaphylactic shock, severe allergic reaction, allergic shock, anaphylactic reaction
- Specialty
- Internal medicine · Critical care & emergency medicine
- Images
- Clinical 1
- Last updated
- 10/2026 · Dr. Pascal Bafteh
Contents
Images (1)
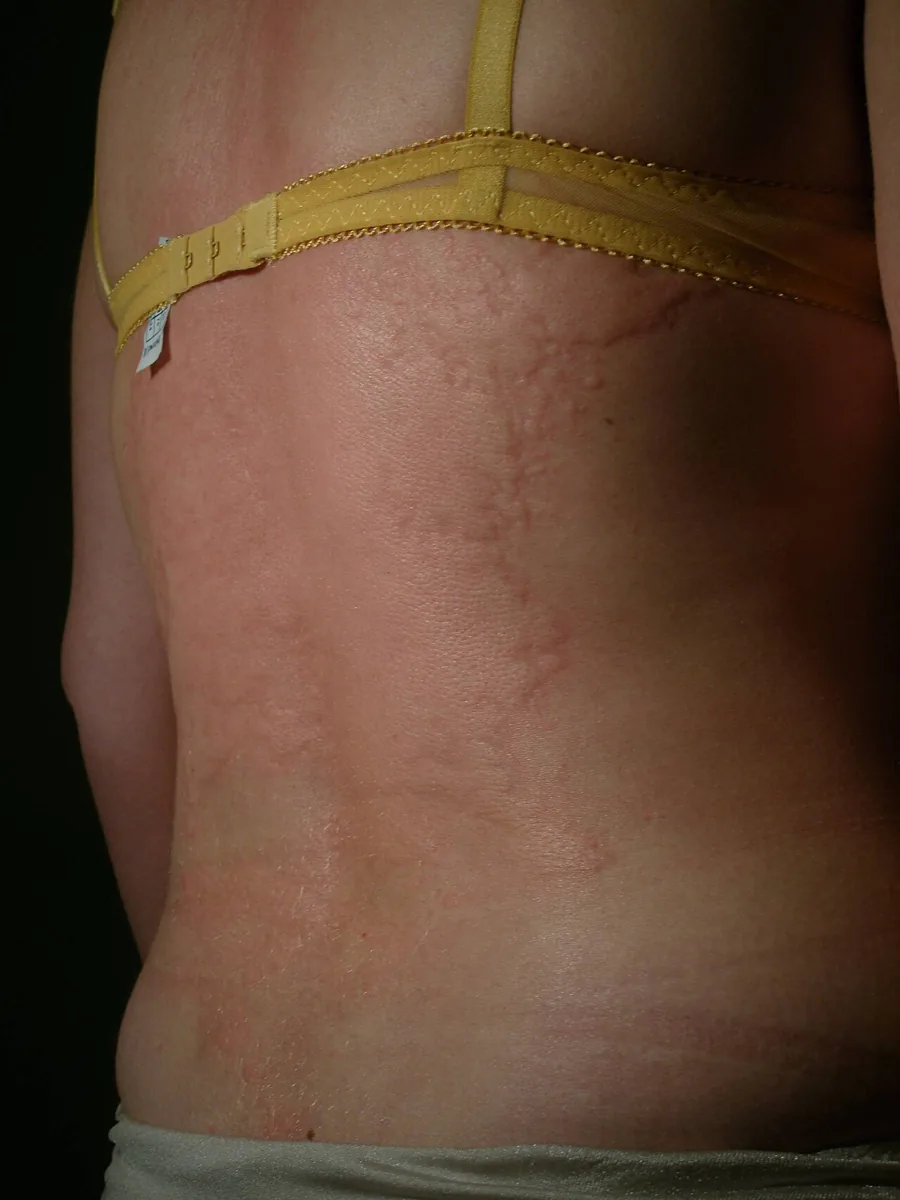
Definition
Anaphylaxis is a serious, systemic hypersensitivity reaction that is usually rapid in onset and can compromise breathing and/or circulation in a life-threatening way. It mainly affects the skin, airways, gastrointestinal tract and cardiovascular system.
Anaphylactic shock is the hemodynamically most severe form with circulatory failure (hypotension and/or signs of end-organ hypoperfusion). All anaphylactic shock is anaphylaxis, but not all anaphylaxis leads to shock.
Classification
In Germany, anaphylaxis is classified into four severity grades according to the most severe symptoms present (modified after Ring and Messmer; no symptom is obligatory):
- Grade I: itching, flush, urticaria, angiedema
- Grade II: additionally nausea, cramps, vomiting; rhinorrhoea, hoarseness, breathlessness; tachycardia (increase above 20/min), drop in blood pressure (systolic more than 20 mmHg), arrhythmia
- Grade III: vomiting, defecation; laryngeal edema, bronchospasm, cyanosis; shock
- Grade IV: respiratory and/or cardiac arrest
By mechanism, the usually IgE-mediated allergic anaphylaxis is distinguished from non-allergic (formerly “anaphylactoid”) reactions that do not require prior sensitisation.
Occurrence & epidemiology
The lifetime prevalence is estimated at 1.6–5.1 %. Studies from the USA, the UK and Australia show incidences of 7–50 per 100,000 population per year, with an increase in recent decades.
Most common triggers of severe reactions in the German-speaking anaphylaxis registry:
- Children: food 60 %, insect venom 22 %, drugs 7 %
- Adults: insect venom 52 %, drugs 22 %, food 16 %
In childhood boys are affected more often; after puberty the sex distribution evens out.
Aetiopathogenesis
Triggers:
- food (e.g. nuts, eggs, seafood; peanut and fish are considered highly potent allergens)
- insect venom (stinging insects)
- drugs (e.g. NSAIDs, beta-lactams, allergen extracts)
- radiocontrast media and other chemicals
- physical factors such as cold and exertion
- unknown (idiopathic)
Pathophysiology: usually an IgE-mediated allergy is the basis. The allergen cross-links IgE on mast cells and basophils, which then release histamine, prostaglandins, leukotrienes, tryptase, platelet-activating factor and other mediators. This results in smooth muscle contraction (bronchoconstriction, vomiting, diarrhea) and vasodilation with plasma leakage (urticaria, angiedema). Non-allergic reactions arise from direct mast cell activation (e.g. via the MRGPRX2 receptor) or complement activation, frequently caused by iodinated contrast media, NSAIDs or monoclonal antibodies.
Augmenting and risk factors: physical exertion (e.g. food-dependent exercise-induced anaphylaxis, usually due to wheat), alcohol, psychological stress, infections; for severe reactions older age, severe cardiovascular disease, poorly controlled asthma, mastocytosis or raised baseline serum tryptase, and certain antihypertensive drugs.
Clinical features
Symptoms usually begin within 15 minutes of exposure to the trigger and can progress to shock within minutes; however, the reaction can also stop spontaneously at any stage. Circulatory reactions can occur without preceding skin or airway symptoms.
- Prodromes: itching or burning of the palms, soles or genital area, metallic taste, anxiety, headache, disorientation
- Skin and mucosa (most often affected): itching, flush, urticaria, angiedema
- Airways: burning or tingling of the tongue and palate, swelling of the uvula and tongue, muffled speech, difficulty swallowing, inspiratory stridor, sneezing, rhinorrhoea, breathlessness, wheezing, cyanosis
- Gastrointestinal tract: nausea, abdominal cramps, vomiting, diarrhea
- Cardiovascular: palpitations, tachycardia, hypotension, dizziness, syncope, shock up to cardiac arrest
- General: restlessness, a “sense of impending doom”; in toddlers often restlessness or reclusive behavior
In 5–20 % of cases, protracted or biphasic courses occur, with recurrent symptoms usually after 6–24 hours.
Diagnosis
The diagnosis is clinical. Anaphylaxis is considered highly likely when one of the following criteria is met:
- sudden skin or mucosal symptoms (e.g. urticaria, angiedema, flush) together with respiratory symptoms (e.g. breathlessness, wheezing, stridor) or a drop in blood pressure or its consequences (e.g. collapse, incontinence)
- sudden symptoms in two or more organ systems (skin, gastrointestinal tract, airways, circulation) after contact with a likely allergen or trigger
- drop in blood pressure after contact with an allergen or trigger known to the person
- Serum tryptase: ideally measured about 1–3 hours after the onset of the reaction, if possible compared with baseline serum tryptase; it can also be measured retrospectively but need not be raised (often normal in children with food anaphylaxis)
- Search for the cause: careful history of foods, insect stings, drugs and cofactors; in healthcare workers with unexplained anaphylaxis, consider latex allergy
Keep learning in the app
Further reading (open access)
Cross-references
More topics: Critical care & emergency medicine
Note: Learning content for medical education – not a treatment recommendation and no substitute for diagnosis or treatment decisions in individual cases. Treatment and management are deliberately not covered on this page.